

SETTING THE PACE WITH
AVEIR™ LEADLESS
PACEMAKERS
AVEIR™ LEADLESS
PACEMAKERS
The only leadless solutions that can provide therapy
for all common pacemaker indications1,2,3
AVEIR™ LEADLESS PACEMAKERS (LPs) ARE THE ONLY LEADLESS SOLUTIONS THAT CAN PROVIDE THERAPY FOR ALL COMMON PACEMAKER INDICATIONS1,2,3
AVEIR™ AR2 ATRIAL LEADLESS PACEMAKER (LP)
- Sinus node dysfunction (SND) and normal atrioventricular (AV) and intraventricular conduction systems
Compare the clinical performance of AVEIR AR2 Atrial LP vs dual-chamber transvenous pacemakers
FIND OUT MORE ABOUT:
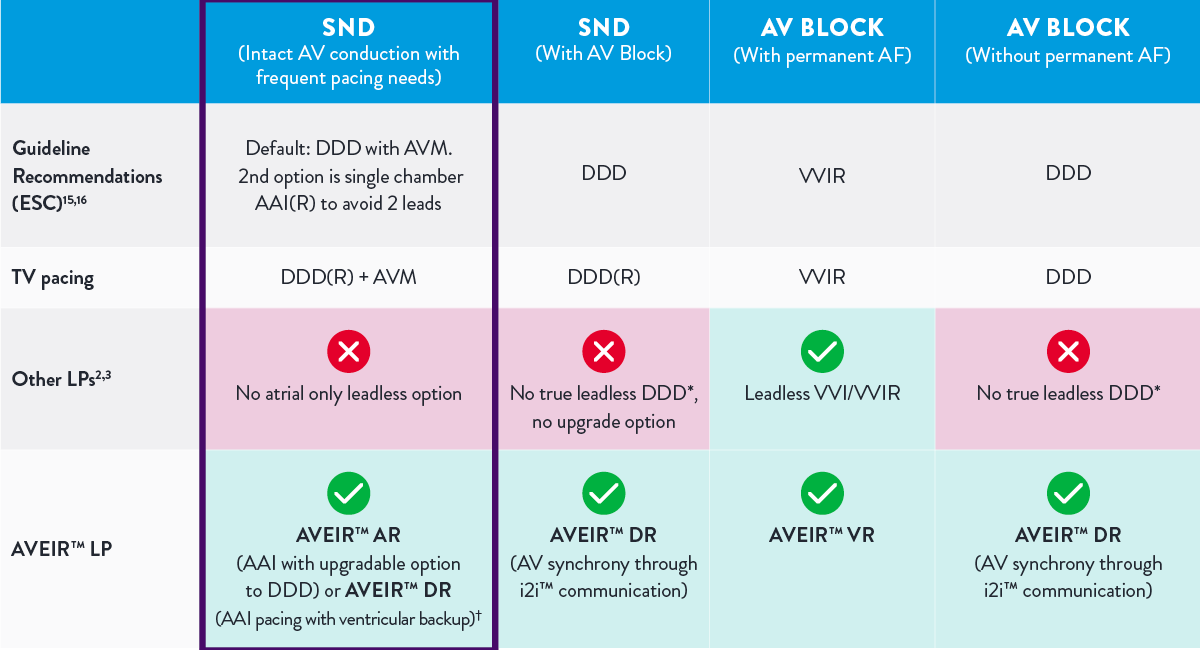
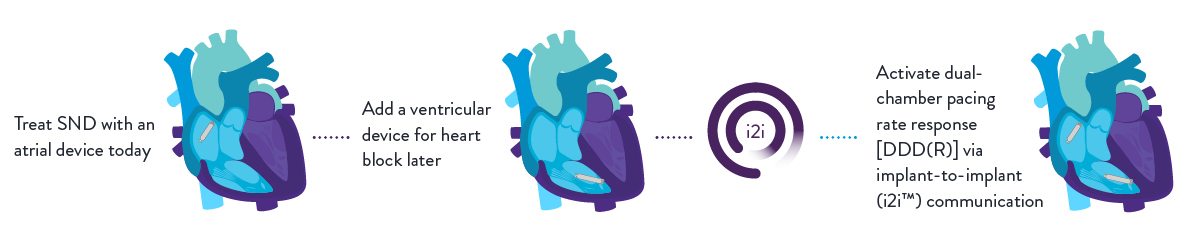
Upgradeable system1,6
The complete solution for SND patients
TAILORED THERAPY FOR SND PATIENTS
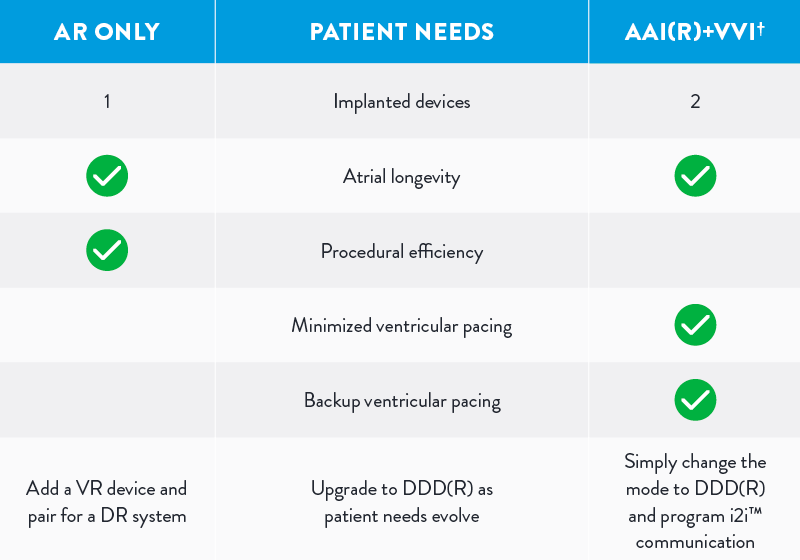
INTRODUCING AAI(R)+VVI†: PROGRAMMING THAT PROVIDES LONGEVITY AND FLEXIBILITY10,18
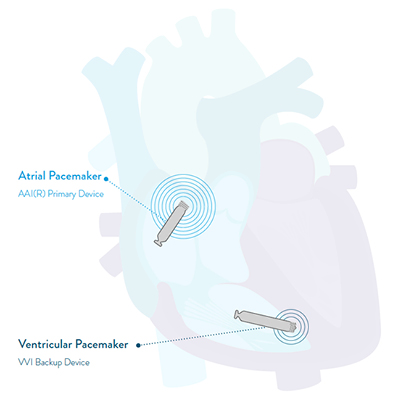
Atrial pacing rate response + single chamber ventricular [AAI(R)+VVI†] mode establishes two independently programmable devices (AVEIR™ AR2 Atrial LP and AVEIR™ VR Ventricular LP)
- i2i™ communication is disabled, resulting in increased battery longevity for both devices
- Program the atrial device for primary support and the ventricular device to a backup rate
- Software update also includes increased pulse width programmability for better fine-tuning of pacing outputs
OVER 10 YEARS OF PROJECTED BATTERY LIFE FOR SND PATIENTS [AAI(R) AND AAI(R)+VVI†]1*
With AVEIR™ AR2 Atrial LP, Abbott advances leadless pacing therapy for better patient care.
- AAI(R) & AAI(R)+VVI† modes: Up to 12.4 years battery life redefines the standard for leadless pacing for treating SND patients1
- Dual-chamber DDD(R): ~8.6 years, comparable to transvenous pacemaker systems
| MODE** | ATRIAL PACING | PROJECTED ATRIAL DEVICE LONGEVITY (YEARS)1 |
|---|---|---|
| AAI(R), AAI(R)+VVI† | 100% | 12.4 |
| DDD(R)*** | 50% | 8.6 |
Connext
TV
TV
TV

Understanding AVEIR VR Retrieval

Why Leadless Pacing Summit 2026 Matters

AVEIR Atrial LP AAI Implant Training Supplement

AVEIR DR Virtual Implant Training Supplement

Leadless in Congenital Patients

When Patients Evolve: Upgradability in Leadless

Optimizing Tricuspid Valve Crossing: Case example

Optimizing Tricuspid Valve Crossing: Case example

Health Economics of Leadless Therapy

Learn AVEIR Leadless Pacemaker Follow-Up Checks
References
- AVEIR™ Leadless Pacemakers and Delivery Catheter IFU. ARTEN600361108.
- Micra‡ VR2 MC2VR01 IFU.
- Micra‡ AV2 MC2AVR1 IFU.
- Udo EO, Zuithoff NP, van Hemel NM, et al. Incidence and predictors of short- and long-term complications in pacemaker therapy: the FOLLOWPACE study. Heart Rhythm. 2012;9(5):728-35. doi: 10.1016/j.hrthm.2011.12.014.
- Cantillon DJ, Exner DV, Badie N, et al. Complications and Health Care Costs Associated With Transvenous Cardiac Pacemakers in a Nationwide Assessment. JACC Clin Electrophysiol. 2017;3(11):1296-1305. doi: 10.1016/j.jacep.2017.05.007.
- AVEIR Leadless Pacemakers and Delivery Catheter IFU. ARTEN600307044. ARTEN600350965.
- Cha YM, El-Chami MF, Liu CF, et al. 2026 HRS/AHA/APHRS/EHRA/IDSA/LAHRS/PACES/STS expert consensus statement update on cardiovascular implantable electronic device lead management and extraction. Heart Rhythm. 2026;S1547-5271(26)02264-2. doi: 10.1016/j.hrthm.2026.04.015.
- Boersma LV, El‑Chami M, Steinwender C, et al. Practical considerations, indications, and future perspectives for leadless and extravascular cardiac implantable electronic devices: a position paper by EHRA/HRS/LAHRS/APHRS. Europace. 2022;24(10):1691‑1708. doi:10.1093/europace/euac066.
- National Institute for Health and Care Excellence (NICE). Leadless cardiac pacemaker implantation for bradyarrhythmias. Health Technology Guidance HTG770. Feb 25, 2026. Accessed June 16, 2026. https://www.nice.org.uk/guidance/htg770.
- AVEIR Leadless Pacemakers and Delivery Catheter IFU. ARTEN600175957; ARTEN600307044; ARTEN600361109.
- Nilsson KR Jr, Birgersdotter-Green U, Saleem-Talib S, et al. Leadless atrial versus transvenous pacing for sinus node dysfunction: 1-year outcomes from the leadless ARRIVE real-world study. Europace. 2026;28(4):euag072. doi: 10.1093/europace/euag072.
- Ip JE, Brady PA, Kroman AM, et al. Leadless Versus Transvenous Single-Chamber Ventricular Pacemakers: Real-World Evidence From AVEIR™ VR Coverage With Evidence Development Study. J Am Heart Assoc. 2025;14(21):e042471. doi: 10.1161/JAHA. 125.042471.
- Lo M, Amin AK, Kowalski M, et al. Leadless Versus Transvenous Dual-Chamber Pacemakers: Real-World Evidence From AVEIR DR Coverage With Evidence Development Study. J Cardiovasc Electrophysiol. 2026;37(3):544-553. doi: 10.1111/jce.70255.
- Neuzil P, Exner DV, Knops RE, et al. Worldwide Chronic Retrieval Experience of Helix-Fixation Leadless Cardiac Pacemakers. J Am Coll Cardiol. 2025;85(11):1111-1120. doi: 10.1016/j.jacc.2024.10.094.
- Glikson M, Nielsen JC, Kronborg MB, et al. 2021 ESC Guidelines on cardiac pacing and cardiac resynchronization therapy. Eur Heart J. 2021;42(35):3427-3520. doi: 10.1093/eurheartj/ehab364. Erratum in: Eur Heart J. 2022 May 1;43(17):1651. doi: 10.1093/eurheartj/ehac075.
- Kusumoto FM, Schoenfeld MH, Barrett C, et al. 2018 ACC/AHA/HRS Guideline on the Evaluation and Management of Patients With Bradycardia and Cardiac Conduction Delay: Executive Summary: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines, and the Heart Rhythm Society. J Am Coll Cardiol. 2019;74(7):932-987. doi: 10.1016/j.jacc.2018.10.043. Erratum in: J Am Coll Cardiol. 2019;74(7):1014-1016. doi: 10.1016/j.jacc.2019.06.046.
- Breeman KTN, Dijkshoorn LA, Wilde AAM, et al. Predicted Need for Atrial and Ventricular Pacing Per Indication Group in Patients With Dual-Chamber Pacemakers. Heart Lung Circ. 2023;32(5):629-637. doi: 10.1016/j.hlc.2023.02.007. Erratum in: Heart Lung Circ. 2024;33(2):e17. doi: 10.1016/j.hlc.2024.01.003.
- Ip JE, Cheung JW , Liu CF , et al. Maximizing battery longevity of leadless pacemaker systems by optimizing individualized programming. Heart Rhythm. 2026;23(2):e293-e294. doi: 10.1016/j.hrthm.2025.10.021.
- Vogt ML, Kellmann T, Ihara Z. Patient’s lifetime budget impact of a leadless pacemaker compared to transvenous pacemakers in France. Poster presented at: European Heart Rhythm Association; April 12-14, 2026; Paris.