

RESYNCHRONIZATION
THERAPY DEVICES
Cardiac resynchronization therapy (CRT) is a proven
clinical treatment for heart failure management.
QUARTET™ QUADRIPOLAR LV LEADS
Offers superb deliverability with exceptional stability and performance. With four electrodes and up to 14 pacing configurations, the quadripolar system enables left ventricular (LV) pacing at the preferred site without compromising lead stability.16
POTENTIAL BENEFITS OF QUADRIPOLAR TECHNOLOGY
- Shorter implant times and decreased fluoroscopic exposure17,18
- Fewer surgical revisions19
- More basal pacing opportunities (pacing basally has been shown to be associated with improved outcomes)20,21
Overall, quadripolar technology can lead to greater cardiac resynchronization therapy (CRT) implant and postoperative efficiencies while providing improved CRT efficacy.
CRT using biventricular pacing (BiVP) is an effective treatment, however, patients who do not respond are at a significantly higher risk of death and heart failure-related hospitalizations compared with CRT responders.
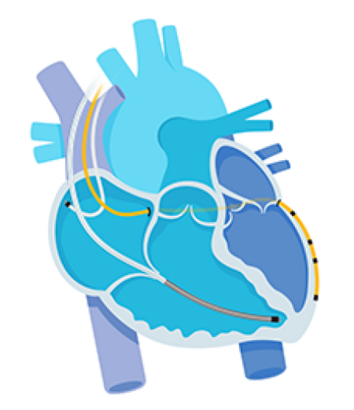
Instead of pacing the left ventricle (LV) from a single site, MultiPoint™ Pacing (MPP) delivers multiple LV pacing pulses per cardiac cycle from along the Quartet™ Quadripolar LV lead, in both LV only and biventricular (BiV) pacing modes.
The MORE-CRT MPP trial is one of the largest prospective, multicenter, randomized controlled trials designed to assess clinical response in patients indicated to CRT.12
The results from the secondary analysis show that MPP, in patients who do not respond to BiVP, is associated with clinically relevant and statistically significant reduction of hard endpoints, such as heart failure (HF) hospitalizations or all-cause mortality.13
Unlock the MORE-CRT MPP potential with the QUARTET™ QUADRIPOLAR LV LEADS
LEARN MORE:
MULTIPOINT™ PACING IN CRT
Understand how advanced visualization of electrical activation can improve outcomes.
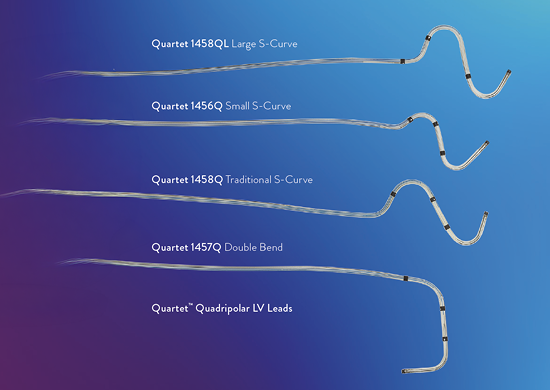
Built on the proven QuickFlex™ (micro) μ lead platform, the Quartet™ Quadripolar LV Lead offers superb deliverability with exceptional stability and performance. Studies reflect an implant success rate averaging approximately 97%.17,19
MULTIPLE SHAPE AND SPACING OPTIONS
- Distal shape options include the Double Bend shape, Traditional S-shape, Traditional S-shape—wide spacing and Small S-shape
- Total electrode spacing options include 40, 47 and 60 mm
OPTIM™ LEAD INSULATION
- First-of-its-kind hybrid insulation material
- Developed specifically for cardiac lead use
- Blends the biostability and flexibility of high-performance silicone rubber with the strength, tear resistance and abrasion resistance of polyurethane, allowing for superior abrasion resistance in a thin diameter lead22
STEERABLE TIP
Adjustable distal tip angle for enhanced maneuverability in venous anatomy
FOUR DISTINCTLY SPACED ELECTRODES
- Enables greater pacing flexibility than unipolar or bipolar leads
- Provides more options to help prevent pacing complications

IS4 CONNECTOR
Enables four pacing electrodes in a single connector for streamlined implantation
LOW PROFILE
- 4.7 French size (F) lead body diameter for maneuverability
- 4.0 F tip electrode, which aids access to small targets or difficult-to-reach branch veins
MRI READINESS
The Quartet Quadripolar LV Lead, when combined with approved devices, allows full-body, 1.5 Tesla (T) and 3T Magnetic Resonance Imaging (MRI) scans that meet certain scan conditions.*
- Meets industry-standard MRI testing requirements
- Capable of full body 1.5T and 3T MRI imaging scans
Hub
TV

MORE-CRT MPP Video

Video Pfeiffer and markus Stühlinger

Video Pedro Marques + Ana Bernardes

The role of CRT - Carsten Israel

Optimizing CRT: From Conventional to LOT CRT
- Thibault B, Waddingham P, Badie N, et al. Acute Electrical Synchronization Achieved With Dynamic Atrioventricular Delays During Biventricular and Left Ventricular MultiPoint Pacing. CJC Open. 2024;7(2):166-175. doi: 10.1016/j.cjco.2024.11.003.
- Calò L, De Ruvo E, Kolb C, et al. Multipoint pacing is associated with improved prognosis and cardiac resynchronization therapy response: MORE-CRT MPP randomized study secondary analyses. Europace. 2024;26(11):euae259. doi: 10.1093/europace/euae259. Erratum in: Europace. 2025;27(2):euaf022. doi: 10.1093/europace/euaf022.
- Katcher M, Davis K, Badie N, et al. Improved ICD Shock Efficacy using Programmable Pulse Width. Presented at: Heart Rhythm Society; April 24-27, 2025.
- Swerdlow CD , Brewer JE, Kass RM, et al. Application of models of defibrillation to human defibrillation data: implications for optimizing implantable defibrillator capacitance. Circulation. 1997;96(9):2813-22. doi: 10.1161/01.cir .96.9.2813.
- Ellenbogen K, Wilkoff G, Kay G, et al. (2007). Clinical Cardiac Pacing, Defibrillation, and Resynchronization Therapy (3rd ed.). Elsevier Saunders; 542-547. ISBN-13: 978-1- 4160-2536-8.
- Kawata U , Birgersdotter-Green U . (2018). Ventricular Fibrillation and Defibrillation, Encyclopedia of Cardiovascular Research and Medicine. Elsevier, 674-682. ISBN 9780128051542. doi: 10.1016/B978-0-12-809657-4.99764-3.
- Efimov I, Kroll M, Tchou P . (2009). Cardiac Bioelectric Therapy. Springer, 468-472. ISBN 978-0-387-79403-7.
- Kroll M, Lehmann M. (1996). Implantable Cardioverter Defibrillator Therapy. Kluwher Academic Publishers, 68 -69.
- Gold MR, Shorofsky SR. Strength-duration relationship for human transvenous defibrillation. Circulation. 1997;96(10):3517-20. doi: 10.1161/01.cir .96.10.3517.
- Kroll MW , Swerdlow CD . Optimizing defibrillation waveforms for ICDs. J Interv Card Electrophysiol. 2007;18(3):247-63. doi: 10.1007/s10840-007-9095-z.
- Doshi SK, Pittaro MD , Reeves R, et al. Efficacy of tuned waveforms based on different membrane time constants on defibrillation thresholds: primary results from the POWER trial. Pacing Clin Electrophysiol. 2012;35(10):1253-61. doi: 10.1111/j. 1540-8159.2012.03500.x.
- Leclercq C, Burri H, Delnoy PP, et al. Cardiac resynchronization therapy non-responder to responder conversion rate in the MORE-CRT MPP trial. Europace. 2023;25(10):euad294. doi: 10.1093/europace/euad294.
- Leclercq C, Burri H, Calò L, et al. Multipoint pacing is associated with reduction of heart failure hospitalizations or death in patients who do not respond to cardiac resynchronization therapy: results of the MORE-CRT MPP randomized trial. Europace. 2025;27(6):euaf070. doi: 10.1093/europace/euaf070.
- Piorkowski C, et al. Early real-world adoption of mobile remote monitoring using the Confirm Rx Insertable Cardiac Monitor. Poster presented at: Asia Pacific Heart Rhythm Society; 2018.
- Device IFUs: Abbott Tachycardia Devices Help Manual (ARTEN600307504A), Medtronic manuals (Evera‡ XT, Amplia‡, Cobalt‡ XT, and Crome‡), Boston Scientific manuals (NG4 Tachy ICD, NG4 Tachy CRT-D), and Biotronik (Rivacor‡ ICDs and CRT-Ds, Acticor‡ ICDs and CRT-Ds).
- Data compiled from clinical study results, on file at St. Jude Medical in Report 60034670.
- Sperzel J, Dänschel W, Gutleben KJ, et al. First prospective, multi-centre clinical experience with a novel left ventricular quadripolar lead. Europace. 2012;14(3):365-72. doi: 10.1093/europace/eur322.
- Duray GZ, Hohnloser SH, Israel CW. Coronary sinus side branches for cardiac resynchronization therapy: prospective evaluation of availability, implant success, and procedural determinants. J Cardiovasc Electrophysiol. 2008;19(5):489-94. doi: 10.1111/j.1540-8167.2007.01096.x.
- Forleo GB, Della Rocca DG, Papavasileiou LP, et al. Left ventricular pacing with a new quadripolar transvenous lead for CRT: early results of a prospective comparison with conventional implant outcomes. Heart Rhythm. 2011;8(1):31-7. doi: 10.1016/j.hrthm.2010.09.076.
- Singh JP, Klein HU, Huang DT, et al. Left ventricular lead position and clinical outcome in the multicenter automatic defibrillator implantation trial-cardiac resynchronization therapy (MADIT-CRT) trial. Circulation. 2011;123(11):1159-66. doi: 10.1161/CIRCULATIONAHA.110.000646.
- Merchant FM, Heist EK, McCarty D, et al. Impact of segmental left ventricle lead position on cardiac resynchronization therapy outcomes. Heart Rhythm. 2010;7(5):639-44. doi: 10.1016/j.hrthm.2010.01.035.
- Jenney C, Tan J, Karicherla A, et al. A new insulation material for cardiac leads with potential for improved performance. Heart Rhythm. 2005;2(5): S318-319. doi:10.1016/j. hrthm.2005.02.1004.